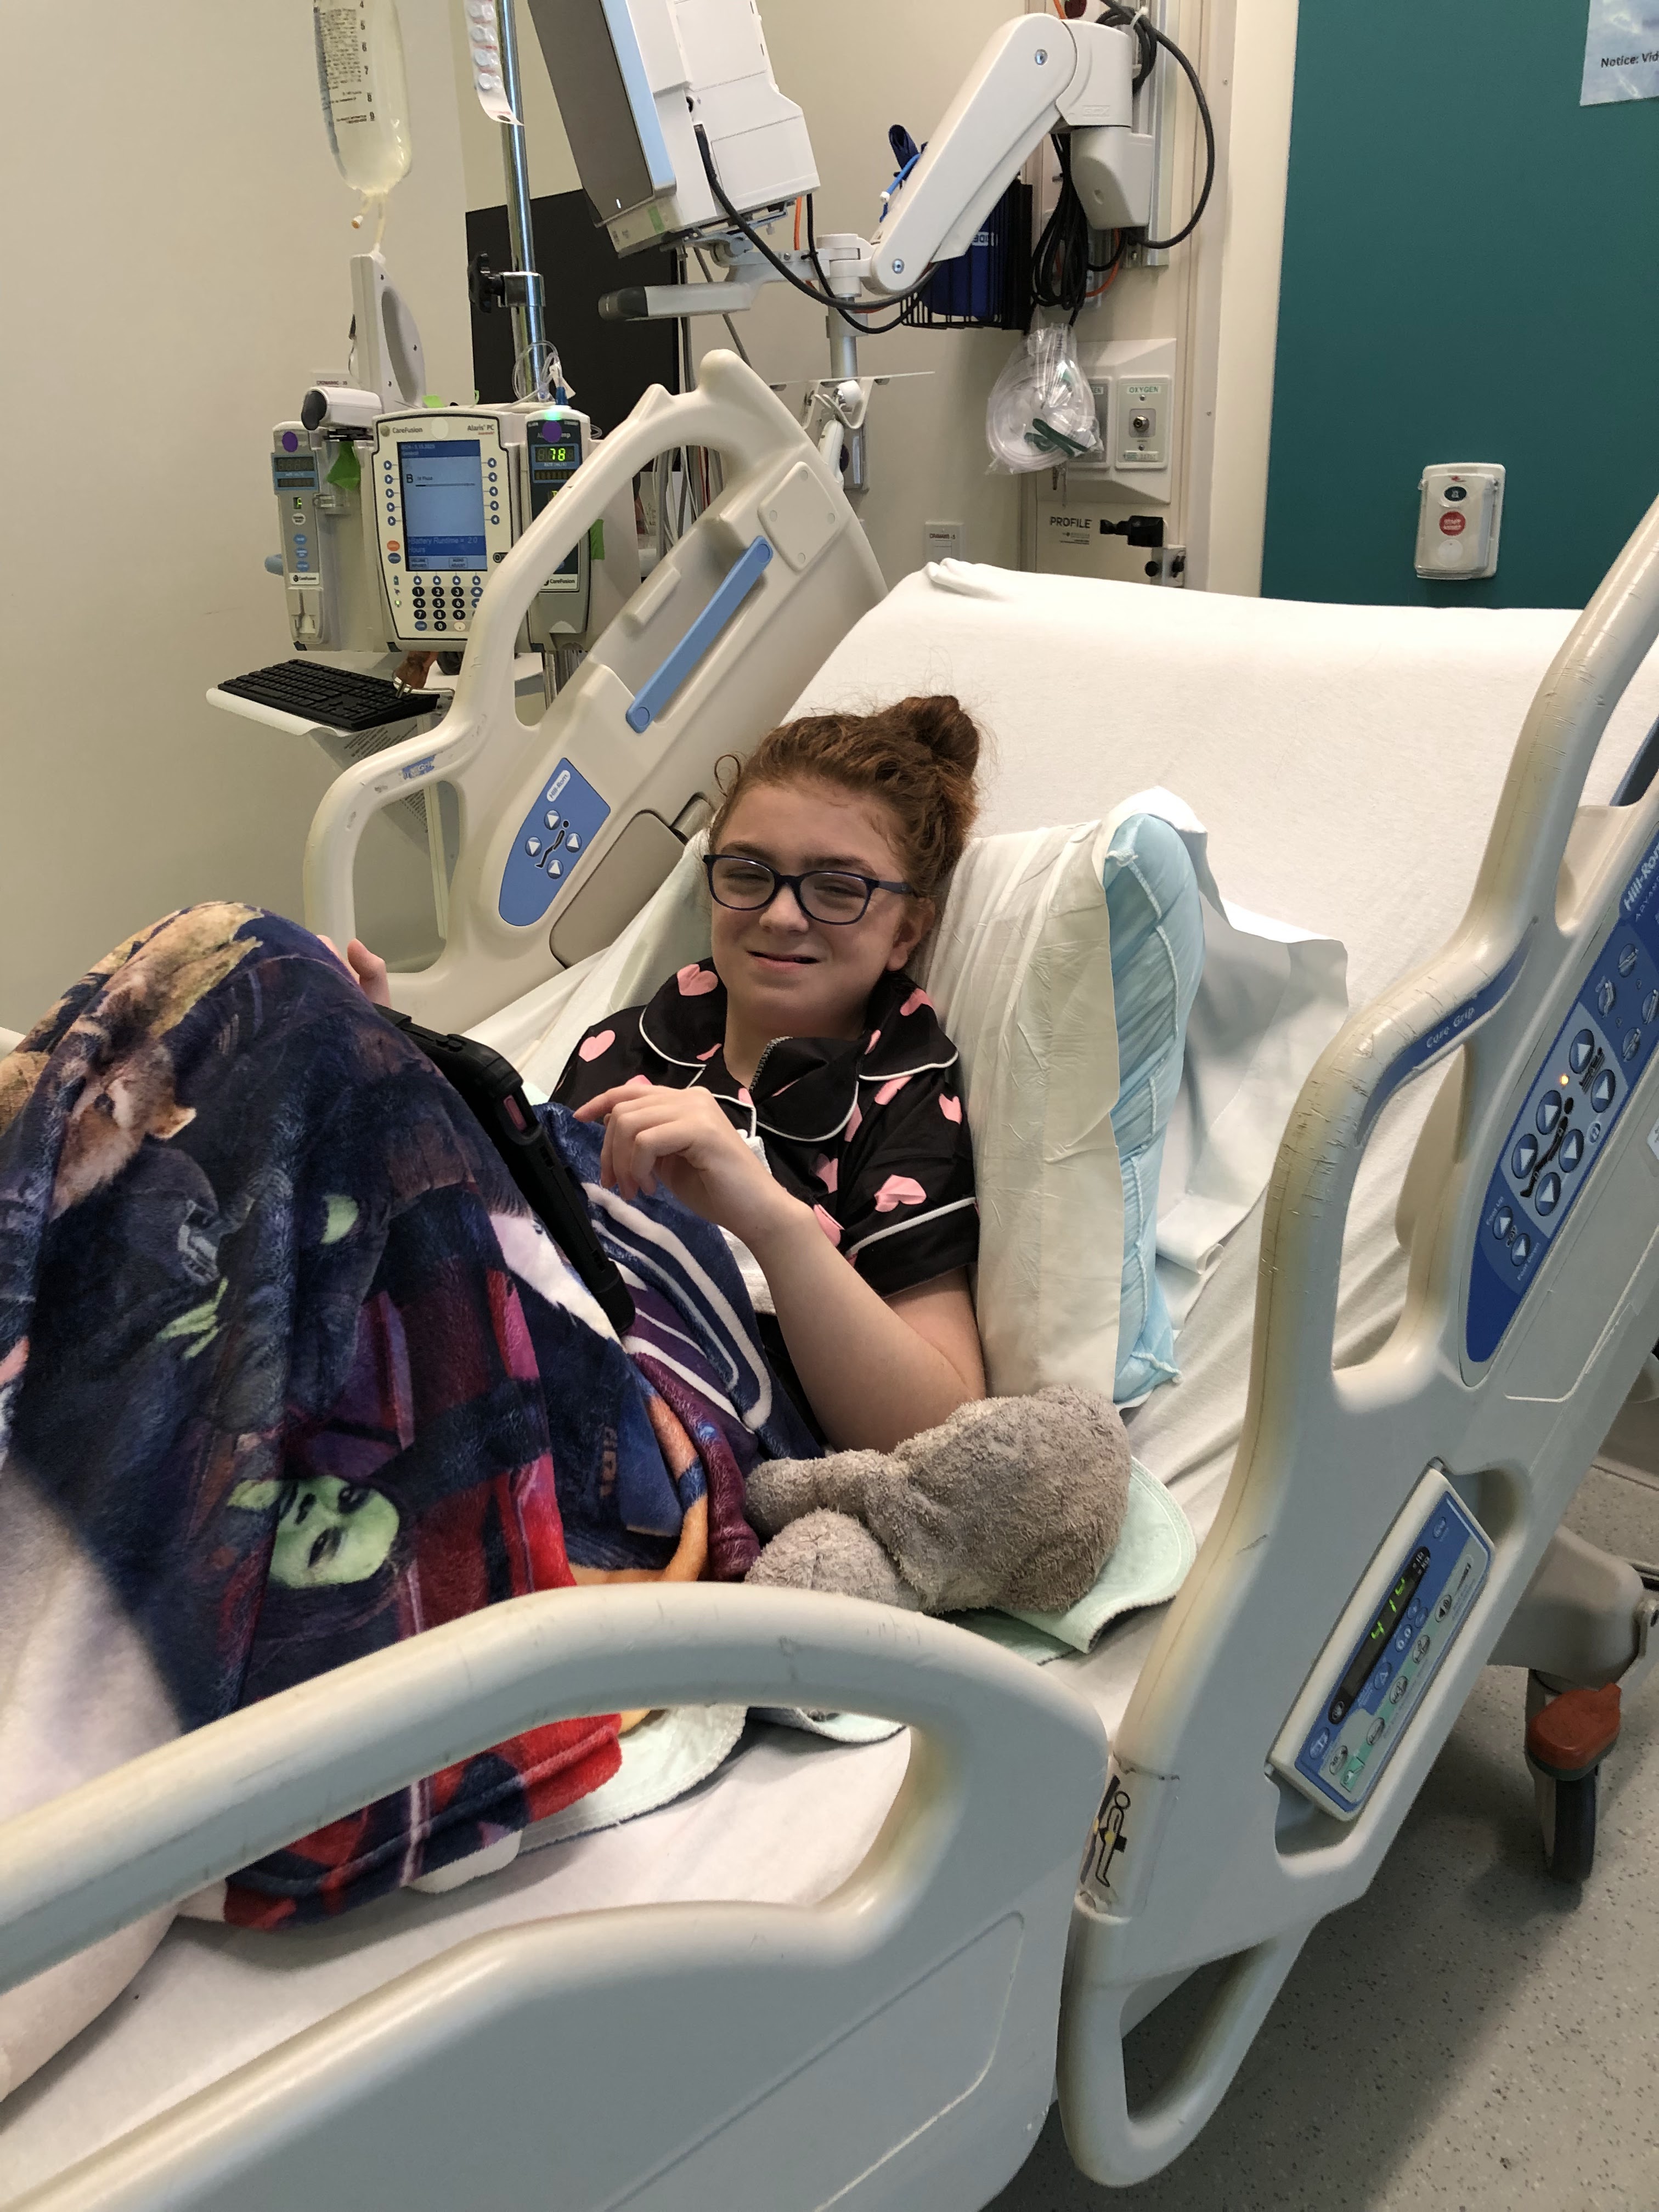
There is a common refrain with parents whose child has special needs:
I want to live one day longer than my child.
One more way this life with Bridget is different than my life with her sister.
With Bridget’s latest PACS1 hurdle this year, one of my biggest struggles was knowing that if she was in a residential program, if I was not in her life every day was knowing in my soul that the catatonia would have gone unreported and untreated.
That is not saying I am perfect or the only one that cares for Bridget. But I am her natural historian. I am the keeper of the medical record. I am the one that has developed a relationship with her team (medical, therapeutic and educational) that when I had concerns about her stimming listened to me and kept searching for an answer.
While I have been struggling with the guilt of the treatment course, the larger battle for sanity was going down the rabbit hole of if I was not willing to advocate for her, if I was not so in-tune with Bridget, what would have happened?
And that is why each and every special needs parent hopes to live one day longer than their child.
Because while we have a village, we have support and people who love our child they are not in the day-to-day, they don’t know the medical history or treatments that have been tried and/or adapted for success.
I am lucky, I am not a single parent. Yet as awesome as Bridget’s dad is…I am the primary caregiver and knowledge base. Some days it is a heavy burden, being the keeper of Bridget. I am lucky that I have a husband who does his best to share the load. I have friendships that do whatever I need, in the moment I need it.
Bridget is lucky, because she has a sibling and cousins that have promised to care for her long after I am gone. And as much I am grateful for that, I know it won’t be the same for Bridget. Not because they cannot but because no one really knows what life with Bridget is like and I don’t ever wish her to be a burden.
This summer, we almost lost Bridget again and I realized that I do not want to live one more day than Bridget.
I want to live a week before the grief is too much to bear, living without her.
I want to celebrate Bridget. I want the world to know that the girl who was told she would never did so much more than we ever imagined.
She rolled over
She walked.
She jumped
She talked and convinced an elderly lady at Market Basket that she “needed” the pop-tarts Bridget put in her basket.
She has made friends and an impact.
She has redefined my expectations, once again.
She has battled and is doing her best to win another fight against PACS1
Bridget will always be fighting PACS1.
And that I why I need to live one week longer than she does.
To tell her story, so that her life is not about her struggles but about her impact.
For most parents, going back to school means buying new school supplies (another pair of scissors!), fighting with your child over new sneakers and back-to-school clothes.
For the special needs parent, it means that the IEP season is on us and we have to review the current IEP to see what goals our child have attempted to accomplish, which goals were good on paper but an epic fail in reality, what new goals we want to see our child attempt and the parent concern statement.
The dreaded parent concern statement. How does a parent whose child has significant special needs create a “concern statement”. Our child’s entire being is a concern. Yes, we want the IEP to be a guide of how to address the concerns. But in reality, there is no way this piece of paper is going to address them. Even if we concentrate on what the school team needs to focus on, forgetting about every other aspect of our child’s life, there is not enough ink in the world to truly capture a parent’s concern.
I have been incredibly lucky that since Bridget’s first IEP at 3-years old (before I even knew what an IEP was), the IEP team has always been a true team. Collaborating together to create a document to guide the education and progress of Bridget. In the 13 years since, there really have been only two times that I feel I had to go toe-to-toe with the educators to remind them that while we are a team, I am the Captain of Team Bridget.
Looking back, when Bridget was younger the IEP was about trying to catch her up to her peers. As she aged, and the gap became too obvious to ignore the IEP became a document to relocate Bridget from the traditional school system to a specialized school that is more equipped to fulfill her significant needs.
As she gets older, the IEP becomes less about learning how to read and more about how to stay at a task for increments of time so that she may one day work at a vocation. It is about learning how to hand a card with her information on it in the case she gets lost. How to navigate a crosswalk and parking lot safely.
As her parent, my expectations are sometimes not in alignment with her capacity.
This is why each participant on her IEP team is important and must come into the room to collaborate with kindness.
This morning, before the IEP meeting I addressed the team with this intention:
If my expectations for Bridget are too low (like giving up on her learning to read), they need to tell me. If my expectations are too high (like her working at a job), I need to know that to.
I believe that at times the educators and therapists are afraid to tell the parent that while they adore your child, there is a reason they are not in the traditional public school.
As we worked through the IEP, I realized that Bridget has entered a new era in her life. We are working on function over form. We are working on making her safe, helping her communicate more effectively, and how to navigate a vocational site.
Bridget is learning how to use a visual menu at McDonalds and how to use a gift card to get her strawberry milkshake.
There are still academics being taught, but not in the traditional sense. Instead of learning algebra, Bridget is learning how to follow a recipe with visuals. Instead of learning how to read a novel, Bridget is learning how to follow a visual schedule.
I admit to this being a painful realization, but that pain is easier to bear when I remember this was the child that wasn’t supposed to survived.
And thanks to the time and compassion her IEP team being invested over the past 14 years…
I was sent this meme the other day and it really put this unexpected life in perspective.
As much as I hate, and I mean HATE in JC CAPS, how much Bridget has suffered in her 16 years, she not only survives she triumphs.
While Bridget battles, I admit to faltering when she has to survive the shit storm. Tethered Spinal Cord just after she came off a pediatric walker? Cue the ugly tears and emergency phone call to my BFF. Going to a pre-K all school playdate where she was knocked over on the playground and I lost it and said she was going to be homeschooled. Thankfully, this was a very brief moment until sanity restored regarding my homeschooling lack of patience which was reinforced when Covid shut down the education system.
Every 12-18m the PACS1 gift that keeps on giving creates some other storm that Bridget (and her family) will need to weather. In the past five years, Bridget has triumphed over relocating schools, Achillies tendon surgery, oral surgery and is now fighting catatonia.
Since 2008, Bridget’s battle average is currently 100% kicking PACS1’s ass.
When Bridget was younger, it was so easy to celebrate the milestones that she worked so hard to achieve. She might not have walked, rolled over or jumped on the developmental scale like her more typical peers…eventually she mastered them.
Bridget at field day around age 7. When we never thought she would be able to walk, she hoola-hooped!
When your child is disabled, you start celebrating the tiniest milestones (she ate without choking!) and overcoming at one time seemed like a skill we would have to give up on. And then later once again, her proving us wrong. It would just take more time and be done in a way that we never expected.
With Bridget’s sister, I have always been laid back when it came to transitions. Going from pre-k to kindergarten? That is supposed to happen. No tears. Turning 16 and getting her license. That is the natural progression. I would have been more upset if she did not get her license. When she graduated high school, she had four options: college, a job with an apartment, the military or not my house. And yes, I not only had that conversation with her but with her high school guidance counselor.
With Bridget, her obtaining those “smaller” milestones that were celebrated seem so far away.
Because at some point, you realize this child is never “catching up”.
Bridget will do many things, but she won’t ever get a driver’s license. She will never go to college, and she will never get married or have a family of her own.
She will never get that “first job” that teaches her how to be a member of a productive workforce. She will one day get a job, but it will be more of a life skill and not a lifestyle choice.
Bridget will never get married or have a family. She will always be a part of a family. Living either with us or her sister. But Bridget will never know the joy of seeing her child’s first steps to them graduating college.
Bridget will not go to college. Now with her sister, no one was more surprised that I was when she decided to go to college. I didn’t expect it to be on an iceberg. I didn’t expect this child who wanted to quit school in third grade, become a student on the Dean’s list. Bridget will never get to shock me that way. She will stay in her special ed program until the day before her 22nd birthday. She will not live in a dorm, have a first love or find her career.
This isn’t anyone putting limits on Bridget. It is the reality when your child is forever 4-years-old. That reality keeps getting closer, the older Bridget gets.
Most days that’s okay with her dad and me. Because we do truly know who this child is, she is our forever child who will do great things and bring tremendous joy to not only our lives but to just about everyone she meets.
Then there are those days when you see her classmates from when she was in a typical public school go to prom, get their learners permits and start touring colleges. When we see the photos of homecoming, dances and sporting events. When we are at a restaurant and our hostess or waitress used to be in kindergarten with Bridget.
And in those moments, it hurts just a bit that I cannot tell her IEP team that her choices at graduation are college, the military or not my couch.
One of the most difficult things I am learning in this time of Bridget’s life is discerning what is behavioral versus what aspects of this newest disease is a mental health issue. Looking back (because it is always easier to see what I did wrong than to predict future mistakes), Catatonia began infiltrating our lives last summer.
As with all things Bridget-itis, the small things I either missed or decided were not important or they were becoming a part of her quirky and cute nature. What I thought was behaviors over time became the tools Catatonia used to try to keep my girl in her head and take her out of our world.
Bridget started refusing to leave the house. Going to the grocery store (one of her favorite places) became a negotiation if there wasn’t someone to stay in the car with her. Thinking it was behavioral, I made her push through when there was no other option. I didn’t realize she was having anxiety, and it was mentally painful for her to walk through those doors. Score 1 to Catatonia.
Bridget started talking only to me at home. I thought (at first) it was funny that she would “hide” her face from her dad and whisper to me the answer to whatever he was asking. Instead of being a new behavior, she was having mental anxiety that led to select mutism. Score 2 to Catatonia.
Bridget, while camping, refused to come to the campfire. Spent most of her time not only in the camper, but in her bunk. Bad mom moment, I kind of enjoyed the peace and quiet of camping, reading my book by the fire not having to listen to freaking Doc McStuffins on repeat. Instead, Bridget was showing the first signs of depression. Score 3 to Catatonia.
I asked the Doctor about all of these new diagnoses. If developmentally, Bridget’s brain is 4 years old, what the freak does she have to be depressed or anxious about? Okay, honestly there was a different “f” word in there.
Instead of reprimanding my use of adult language (perks of talking to her psychologist, they’re probably used to much worse), he gently explained that while Bridget’s mind might be 4 years-old, her body is not. Not only is her brain continuing to adapt and fight PACS1, but it is also having to deal with all the other hormonal, body and insert your teenage angst issue here concerns. Since her brain does not know how to deal with all that onslaught, it retreated into a state of catatonia.
Taking a minute here to remind all of you that I am not a doctor and may have misunderstood or misinterpreted all the information the Doctors have thrown at us over the past 4 months. If you have any of these issues or concerns, don’t trust me. Seek medical advice from a medical professional.
Carrying on after that short PSA. The Doctor tried to explain to me that with catatonia, depression, anxiety, select mutism and PACS1 (plus every other diagnosis Bridget has) what I am / have been afraid were behaviors I needed to help her correct, where actual mental health issues that we need to treat.
I asked how to I make sure that I don’t inadvertently create a behavior during this time?
I totally stumped the medical team with that one!
Here is the dilemma, the medical team is treating Bridget the patient. They are treating all the symptoms associated with her new diseases. They are also trying to be caring and cognizant of how her illnesses now affect our lives. (FYI getting up at 6am every day to give her a med SUCKS in JC CAPS, especially on the weekends). Yet they never thought of what behaviors we might create while treating her medical issues.
For example, what if I let Bridget not participate in grocery shopping now, while she is in crisis. What happens when she is no longer in crisis but has a learned behavior of staying in the car with dad? I guess that is okay, if he is home. But what if he is not and I have to run to the pharmacy?
What happens if we isolate ourselves now, to protect her from all her illnesses but that leads to us never leaving the house? (Self-serving PSA–if I am stuck in this house for more than 3 days, not allowed to leave, send Pinot Grigio).
Thankfully, this new cohort of Doctors listen and care. The advice is that if a behavior is not impacting Bridget’s life (like her increased stimming) then it is not a problem. For me not to sweat the small stuff (they are obviously new to the team). The behaviors that do impact her life (not leaving the house) is something we need to focus on. First with medication, then when she is no longer in this crisis “flight” mode, with therapy and baby steps.
And we have begun seeing small wins. Last weekend, Bridget walked to the beach. Score 1 to Bridget.
Today she got off the van very upset because her favorite teacher was not in school today. She verbalized it, and let me hold her until the tears were dry. Score 2 to Bridget
Keeping score, right now catatonia is up 3-2.
I know with time Bridget is going to kick catatonia’s ass. I am just going to have to be vigilant that once she does, there is not another behavior she has to overcome.
If I was a betting person, I would bet on my girl. She has never let me down before.
Last week this memory popped up on my Facebook feed and I had no idea what I had written way back in 2013.
I searched and found this post where I was trying to explain to a four-year-old Bridget (Boo back then) why she had to work so hard to make the tiniest progress and how sorry I was that I am the one that causes her the pain, procedures and therapies. Yet I never once in those four years, have I regretted one moment of this unexpected life.
Unfortunately, for Bridget, turning 16 was not sweet. It has been nine months of struggle and after a lot of work, acquiring not one but four more diagnoses and adding more doctors to her list of specialists.
Which brings me to this moment, where that letter to Bridget needs to be updated. *Tissue warning ahead.
Today is World Rare Disease Day. A day to celebrate this unique life Bridget and our family live. I was honored to share our journey today with a BlueRock Therapeutics, a Therapeutic company and the researchers who may someday change the lives of families who battle rare syndromes. While BlueRock does not study PACS1, they are making headway in other diseases.
I was drafted into the role of a rare disease advocate after the birth of my daughter, Bridget. Truthfully, I did not know this world existed until 14 years ago.
Bridget was born after a normal pregnancy. Shortly after birth, I recall thinking her breathing was funny, like she was scared. We went home, and I recall having Bridget on my knees thinking she was breathing like she was scared. A visiting nurse stopped by a few days later to do a well-check and was concerned by Bridget’s breathing. Thinking back, I honestly was almost cavalier about it. I told her we were taking Bridget to the pediatrician the next week and would mention it to him.
Thankfully the nurse decided to call the pediatrician herself and we were told to drive immediately to Children’s Hospital. This is how relaxed we were, we not only drove to Boston (not calling 911), but we brought her older sister (then 5 years old) and our golden retriever! I had just had a c-section, it was Thanksgiving weekend and thought everyone was overreacting.
I have never been more wrong in my life.
We entered the ER at Childrens and faster than I would have imagined, my 4 day-old baby was hooked up to an EKG machine and oxygen. Around 10pm that night we were told that we would be admitted, my husband left with our older child and I was left not knowing what the heck was happening. At 2 am an ECHO tech arrived and began performing an echo. He immediately called his supervisor and we were transferred to the NICU. Where Bridget gained a lot more doctors and I got a lot more experience at navigating the halls of Children’s Hospital.
After 10 days, Bridget was released home. However this would not be the last time she would visit Hotel Childrens. When Bridget was about 3 months old, we were once again spending a few days at her favorite hospital. A woman walked in and said she was from genetics. She wanted to go over Bridget’s family history. I asked why? Apparently the team was stumped, so they asked Genetics to get involved. None of Bridget’s medical issues correlated to one another. They were hoping to look at genetics to find the answer.
What Genetics found was there was a genetic abnormality, but it came back as “unknown”. Now, imagine as a parent you are told that not only does your daughter have more health issues that were decidedly not in the “What to Expect When You’re Expecting” book, but there was something genetically “wrong” with your child. They could not tell us if she would survive, if she would roll over or if she would talk. We knew nothing.
We were undiagnosed, and okay with that.
From that the moment, I termed it Bridgetitis and decided that since we did not know what it was, it would not limit her.
The next few years were spent throwing every type of therapy imaginable at Bridget. Since they could not tell us what her outcomes would be, we would not let anyone tell us what they would not be. We did physical therapy, occupational, speech and hydrotherapy. We were at the therapy center so often that her therapists became our friends. At 3, we enrolled her in the public schools integrated PK and began ABA therapy. While it took time, Bridget eventually began to walk, she jumped and with a lot of time began to talk. Though it would not be until she was 8 years old that she would have true “speech”.
I began blogging about our journey, desperately trying to find someone like me, a parent who had a child with an undiagnosed syndrome. One day I wrote a piece called “Calling Dr. House”. Bridget had 13 doctors but not one of them looked at the whole child. We had GI, that worked on her reflux. We had neurosurgeon that performed an operation on her spine. We had a neurologist and a developmental delay specialists. So many doctors, but no one talked to another. Genetics seemed to be stumped.
A reader of my blog reached out. She knew of a doctor that would perform EXOME sequencing. As I said, we were trying anything, even if the answer was I don’t know, we wanted to try. We reached out to the doctor who was a clinical biochemical geneticist in Georgia who would provide Exome sequencing, for a price. As this was not covered by our health insurance, we really had to deliberate it. Not only would we have the expense of getting to Georgia, we would have to pay the doctor for her time and then pay the lab fees. We also had a 10 year older sister to consider, who would she stay with while we were away? I researched the doctor, making sure she had credentials, references etc… After doing our due-diligence, we made the trek from the Cape to Atlanta. Dr. Kendall did a thorough exam, ruled out some genetic syndromes immediately and then decided that Bridget should be a candidate for Exome sequencing. We did the testing and went home to await the results.
Fast forward three months. I am sitting at my desk at work and Dr. Kendall calls. She has great news, the Exome testing was able to tell us that Bridget not only has a genetic malformation but what that malformation is. Great! What does she have? PACS1 Dr. Kendall replied. What does that mean, I asked. Her reply? I have no idea. It’s only been seen in two boys in the Netherlands. There was one research paper that she could find.
When I think back to this time, I remember thinking how surreal my life has become. I was at work, it was midday and I had just been given news that changed everything, yet changed nothing.
Of course, I immediately read the PACS1 research paper, that was clearly over my knowledge base. However (and this is where all of you come in), within the paper there was a listing of all the researchers. One of them was from America, a scientist at Duke University. I somehow found his contact information (thank you Google!) and emailed him. I explained how Bridget had just been diagnosed with PACS1, was there any more research going on, did he know anything more than the paper. He responded within hours and was beyond kind. Not only was he kind, he was helpful. He immediately put me into contact with another researcher, who in turn put me into contact with the head of the Study, Janneke Schurrs-Hoeijmakers. Janneke let me know that not only was Bridget, not the 3rd child nor was she the only girl in the world. Bridget was actually the 13th child and the 4th girl to have the syndrome.
What I loved about my interaction with the team of scientists, who did not have to respond at all, was the compassion. One of my favorite quotes from the email sent to me by the professor at Duke was, “I do dream of the day when my response to emails such as yours will be to “take two of these pills and see me in the morning”. He understood how not having the answers not only affected Bridget, but the entire family.
Since 2014, when Bridget received her diagnosis there have now been over 250 children identified as having PACS1. Very limited research is continuing on PACS1, when our numbers are so small, it is hard to get scientists interested. We do have one parent funded research that is in its infancy.
What doctors and scientists should realize is that families are the best source of information. We share everything and notice trends within the group. The parents have learned that it is a mutation that affects multi-systems. PACS1 is a mutation of a protein gene that affects all systems, with varying degrees. For example, all PACS1 children look like siblings with their dysmorphic features, thin lips and button noses. All PACS1 children have an intellectual disability, yet some can read and write while others cannot. Less than half of PACS1 children have epilepsy, yet the majority have reflux and eating issues. As more children are tested, our numbers have grown. We now know that there is no early morbidity as a result of PACS1, the oldest “child” is 38 years old.
We do know that it is not hereditary, so we do not have to worry about future grandchildren or nieces and nephews.
In 14 years of living with Bridget, not one of her specialists has asked how we are doing as a family? They do not seem to understand that Bridget is not the only one diagnosed with PACS1, we all are. Nine years after being diagnosed, we are still on a journey. And the journey is not just Bridget’s, her PACS1 diagnosis affects the entire family.
She has a sister that knows one day she will be responsible to care for her. She has parents that cannot leave her alone to go on a date night. PACS1 affects our finances, for example my husband cannot take overtime if it interferes with my own work schedule. Whereas if Bridget was a teen without PACS1 this would not be an issue. Bridget now goes to a school that has a 45 minute commute, thankfully the school helps with transportation. But if we have to pick her up from school due to a cold, for example it’s not like we can just pop in and continue with our day.
Bridget is going to need lifelong care. She has 14 doctors that need to be seen on a 6m to yearly basis. That means time off of work does not mean to go on vacation but to travel to Boston.
There is also a financial burden, when you have a rare disease. Without insurance, some families face bankruptcy.
I shouldn’t have to preface, but every rare disease parent does: We love our child, but not every day is sunshine and unicorns.
It’s not just the financial impact, but the mental.
When you realize you are still showering your 14 year-old or changing their diaper in the morning. When you realize you cannot go to certain events because you would have to bring your teen, who is actually a 4 year-old with you. When at the grocery store, you have to keep your hand on your child so they don’t disappear.
That you and your partner have to work harder at your marriage than your friends, because there are so many stressors that you can become focused on, you sacrifice your marriage.
It affects the siblings. My older daughter has always known that Bridget would one day live with her. We are incredibly lucky, the girls are extremely close and Abbey has never been jealous. However, I know that this is not the case in a lot of homes. When Dad goes with their typical child and the mom stays home with the PACS1 child. Some siblings resent that they cannot have friends over, or in the middle of the school play their PACS1 sibling acts up and the parents have to leave.
Just like my older child, I do not know what the future is for Bridget. In some ways having a rare syndrome is also having a typical life. Since we don’t know how PACS1 will continue to affect Bridget, just like before she was diagnosed, we do not set limits. We try everything, though soccer was an epic failure, swimming was not! She loves to play mini golf and go sailing, but hates basketball.
Patients like Bridget, have a life outside of their diagnosis. They are a part of the community. One of my mantras is that Bridget will be a part of the village, not the crazy aunt that only comes down for family photos. Yes, PACS1 affects her in so many ways. And as I have said, it also affects the whole family.
But PACS1 does not define Bridget, it just makes her rare.
On April 30, 2017 during our PACS1 Family gathering we were so thankful to have Dr. Wendy Chung join us for a mini-conference. Dr. Chung is a geneticist from Columbia University in NYC. She works with Simons VIP to provide families access to research opportunities, support and information.
Initially, Simons VIP focused on certain copy number variants associated with autism. They have expanded their research to include a wider variety of genetic events that cause neurodevelopmental disorders, (like PACS1). The main goal of Simons VIP is to help provide treatment and care by identifying the genes that cause medical, cognitive and intellectual disabilities. Continue reading →